01 47 20 48 70

French version — the French version is the authoritative one.

Main de chirurgien examinant une poitrine, illustrant un résultat naturel d'augmentation mammaire réalisée par le Dr Pulvermacker à Paris

Breast reconstruction after cancer in Paris 16

The surgical treatment of breast cancer by mastectomy is the removal of the whole breast and the areola, leaving in its place a transverse scar in the middle of the chest.

Reconstructing a breast that has been removed is an essential stage in recovery. To rebuild a breast is to answer positively the injustice that this illness represents. It is a long road, sometimes a difficult one, but it allows each patient to recover a sense of femininity and wellbeing after that ordeal.

Why reconstruct a breast after a mastectomy?

The objective is to restore a shape, a volume and above all a harmony to the chest and the décolleté, after the partial or total removal of a breast.

Reconstruction makes it possible to ease the psychological suffering of that removal and to restore social, personal and intimate peace of mind.

How does follow-up fit with oncological care?

Surgical follow-up does not replace oncological follow-up: it is added to it, and it is coordinated with the team already caring for you. Nurses at the practice and the clinic deliver local care, the anaesthetist follows pain relief, and two review consultations are scheduled, within seven days and between day ten and day fourteen. Manual lymphatic drainage may be indicated, taking account of any previous node clearance or radiotherapy, which change what is appropriate. See post-operative care.

When can reconstruction be carried out?

The consultation with the reconstructive surgeon can take place very early, including just after being told that a mastectomy is necessary, before cancer treatment has even begun. It allows you to picture what comes afterwards.

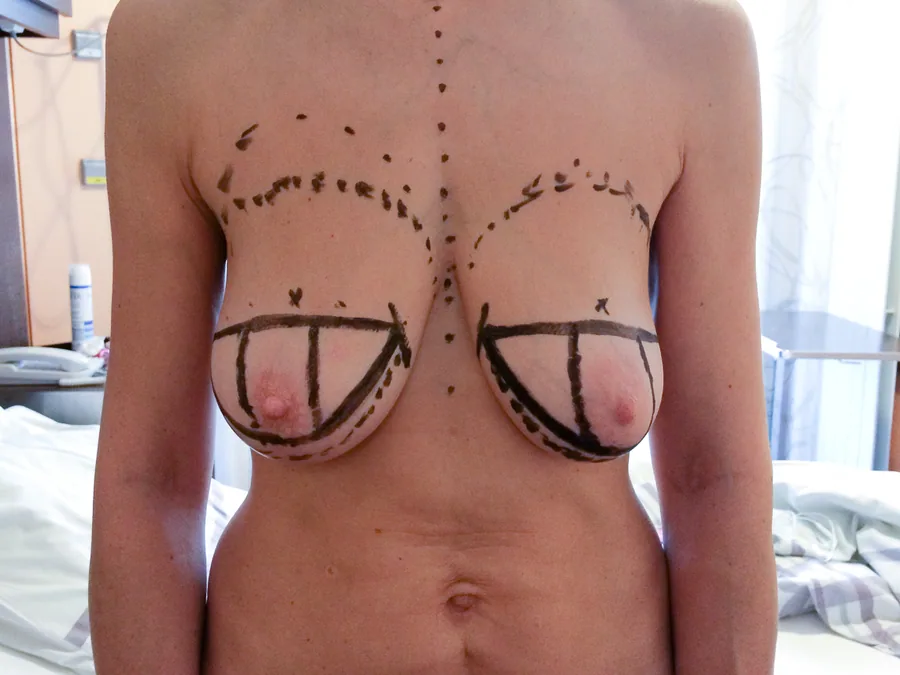
Photo avant reconstruction mammaire - Dr Pulvermacker, Paris

What is immediate breast reconstruction?

In certain cases, immediate reconstruction can be carried out during the same operation as the mastectomy. It will nevertheless require a second stage for the areola.

Immediate reconstruction is possible where no radiotherapy is planned afterwards, since radiotherapy weakens the tissues and compromises the result of a reconstruction already in place.

Which reconstruction techniques exist?

The methods depend on local conditions: the quality and quantity of remaining skin, whether or not radiotherapy has been given, the appearance of the opposite breast, the patient's morphology and, of course, her wishes.

Depending on the case, and sometimes in combination, we use:

  • a breast implant;
  • a latissimus dorsi flap or an abdominal flap (DIEP), where skin is lacking;
  • reinjection of fat (lipofilling).

How are the areola and nipple reconstructed?

Reconstruction of the areola and nipple is the final stage. Most often we use a skin graft taken from the groin fold, reconstruction of the nipple by graft or flap, and tattooing.

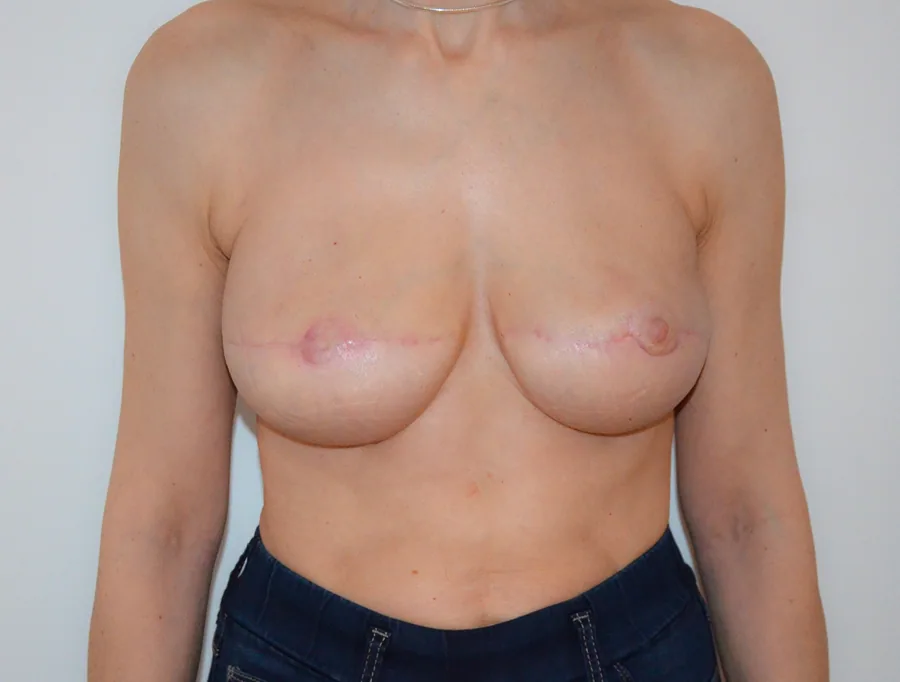
Photo après reconstruction mammaire - Dr Pulvermacker, Paris

Does the other breast need surgery?

In more than 75 % of cases, an operation on the other breast is justified in order to obtain the best possible symmetry. Depending on the case this is a reduction, a correction of ptosis or an augmentation with an implant.

What is the recovery like?

Where reconstruction uses a flap, it is a fairly major operation requiring on average a week in hospital. After a breast implant, three to four nights are necessary. Lipofilling and reconstruction of the areola are carried out as day surgery.

How long does the reconstruction pathway last?

Reconstruction requires at least two operations and extends over a period of six months to a year. The result of each stage is assessed between three and four months, and approving it allows the next one to proceed.

After an immediate reconstruction, care must sometimes be taken that the patient is not disappointed: that she does not imagine she will recover the breast she had before. The period of mourning that follows a mastectomy is often necessary and makes it possible to appreciate the reconstruction more calmly.

From the first stage onwards, the patient gradually recovers a sense of wellbeing in the gestures of daily life and in intimacy. The end of the reconstruction allows this period of her life to be closed and a new one to begin.

What are the risks?

Besides those linked to general anaesthesia, the risks associated with implants placed on irradiated skin deserve emphasis: the fragility of the skin can lead to the scar opening and the implant becoming exposed, in which case it will have to be removed.

Healing problems after a latissimus dorsi or abdominal flap — necrosis, wound breakdown — may occur, which is why tobacco is contraindicated during a breast reconstruction.

The other risks and the technical details of each method are explained in the corresponding SoFCPRE information leaflets.

Is breast reconstruction reimbursed?

Yes. Breast reconstruction after mastectomy comes under reconstructive surgery and is covered by French health insurance, including symmetrisation of the opposite breast and reconstruction of the areola.

Last updated: August 2026 · Medical content reviewed by Dr Benjamin Pulvermacker, board-qualified plastic surgeon in Paris 16.

Who this operation suits — and who it does not

It is for any woman who has had, or is due to have, a mastectomy: reconstruction is a right, fully reimbursed, immediate or delayed, and the choice of timing and technique belongs to the patient. It may not be suitable straight away when ongoing treatment — radiotherapy in particular — means waiting so as not to compromise the result, or when the patient does not wish to be reconstructed, a decision just as worthy of respect and one that can be revisited at any time.

Limits and specific risks

No reconstruction gives back the breast that was there before: it restores a volume and a silhouette, with reduced sensation. Each technique has its own constraints (capsular contracture and further procedures with implants, donor-site scars and long operating times with flaps, multiple sessions with fat transfer alone), and previous radiotherapy changes what is possible. Balancing the other breast and reconstructing the areola complete the process, and are also reimbursed. This path is built in several stages, in coordination with the oncology team.

A question about this procedure ?

Call 01 47 20 48 70

You are still hesitating

A consultation commits you to nothing.

A proportion of consultations end with no indication, or with a decision to wait. These are normal outcomes, and they are said to your face.

What happens at a first consultation →

Consultation

Let us talk about your plan

The secretariat answers from Monday to Friday, 9 a.m. to 6 p.m.

You have decided

Request an appointment

Give your availability, the practice offers you a slot.

My availability

You would rather speak

Be called back

Leave a number and a time. The secretariat calls you within 48 working hours.

Be called back

You are gathering information

Write to the practice

A question, without an appointment. The secretariat passes it on, answer within 48 working hours.

Ask a question

Or by telephone : 01 47 20 48 70Exchanges are covered by medical confidentiality.

A detailed quotation is compulsorily given at the consultation. A statutory reflection period of fifteen days runs from the moment it is handed over.

Let us talk about your plan

The secretariat answers from Monday to Friday. You may also write : we call you back within 48 working hours.

Breast reconstruction after cancer in Paris 16 — a question about this procedure ?Be called backWrite01 47 20 48 70
Call Write