01 47 20 48 70

French version — the French version is the authoritative one.

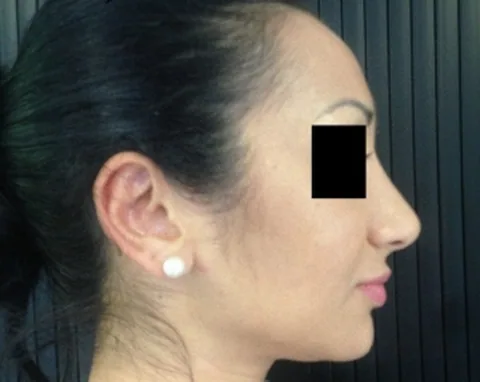
Portrait of a patient with a radiant complexion, illustrating the dermatological surgery provided by Dr Pulvermacker in Paris

Rhinoplasty in Paris 16 — aesthetic nose surgery

The nose gives a face its character. It occupies the centre, it carries the light, and it is the only feature that can be neither styled nor made up. When it does not suit, it ends up being experienced as a foreign body whose presence is a daily irritation.

The aim of a rhinoplasty is not to create a beautiful nose in the absolute: it is to soften the features by making the nose more discreet and more harmonious with the rest of the face. The operation is a delicate one, because it alters the outward appearance of the nose without having to change the person radically.

Some surgeons always make the same nose, whoever the patient, like a signature. For me, who argues for the natural, a successful nose is a nose that does not look as though it has been operated on.

What is a rhinoplasty?

Rhinoplasty alters the bony and cartilaginous structure of the nose: reduction of a dorsal hump, refinement or repositioning of the tip, narrowing of the nostrils, correction of a deviation.

The nose is not a single block. Its upper third is bone, its lower two thirds are cartilage, and the skin covering them changes in thickness from top to bottom. Altering one without accounting for the others produces the results one recognises from across a room: a dorsum hollowed too far under a tip that has stayed broad, or a refined tip under a dorsum that has stayed high.

Where a breathing problem is also present — a deviated nasal septum, the sequela of trauma — the procedure also addresses the septum: this is called a rhinoseptoplasty. That functional component may give entitlement to partial reimbursement, to be discussed at the consultation.

Why consider a rhinoplasty?

Because you dislike your nose so much that you avoid looking in the mirror and can no longer bear to see yourself in photographs.

To remove a hump and soften the profile. Because the tip is felt to be too long, too round or too broad, or because it drops when you smile.

Because the nose brings to mind a family member you would rather not resemble — a frequent and perfectly acceptable motivation.

Because trauma has deviated the nose, sometimes causing breathing difficulties and snoring.

These requests have one thing in common: they are long-standing. A concern that appeared ten years ago and is put into the same words at every consultation is a better indicator than a request born of a recent photograph.

What does the surgeon look at during the consultation?

This is the stage that determines everything else. A nose is not operated on from a photograph taken face-on: it is analysed in three dimensions, in movement, and always in relation to the face that carries it.

The profile, and the part played by the chin

The hump is what the patient points to first. But the prominence of the nasal dorsum is judged against two landmarks: the forehead above, the chin below. A receding chin makes a nose look longer and more prominent than it really is.

This is one of the reasons why I do not commit to a procedure before having looked at the profile as a whole. In some cases a limited correction of the nose is enough; in others it is the overall balance that has to be discussed.

The tip: projection, rotation, definition

Three independent parameters, often conflated under the single word « tip ». Projection is how far the tip stands forward from the face. Rotation is its orientation upwards or downwards — it is what sets the angle between the lip and the nose. Definition is the fineness of the contour.

A tip may be well projected and poorly defined, or fine and drooping. Telling these three apart is what makes it possible to say, at the consultation, what will be changed and what will not.

The thickness of the skin

This is the least visible factor and the most decisive. Thick skin masks the detail of the cartilage: the refinement achieved underneath shows only in part, and the swelling takes longer to settle. Very thin skin, conversely, reveals everything, including the slightest irregularity.

This parameter cannot be corrected. It is stated before the operation, because it sets part of the result that is achievable.

Breathing

Examination of the nasal passages is part of the consultation, even where the request is purely aesthetic. Reducing a nose without checking its internal supports can create a breathing problem that did not exist before. Conversely, an unrecognised deviation sometimes explains a long-standing difficulty the patient had come to regard as normal.


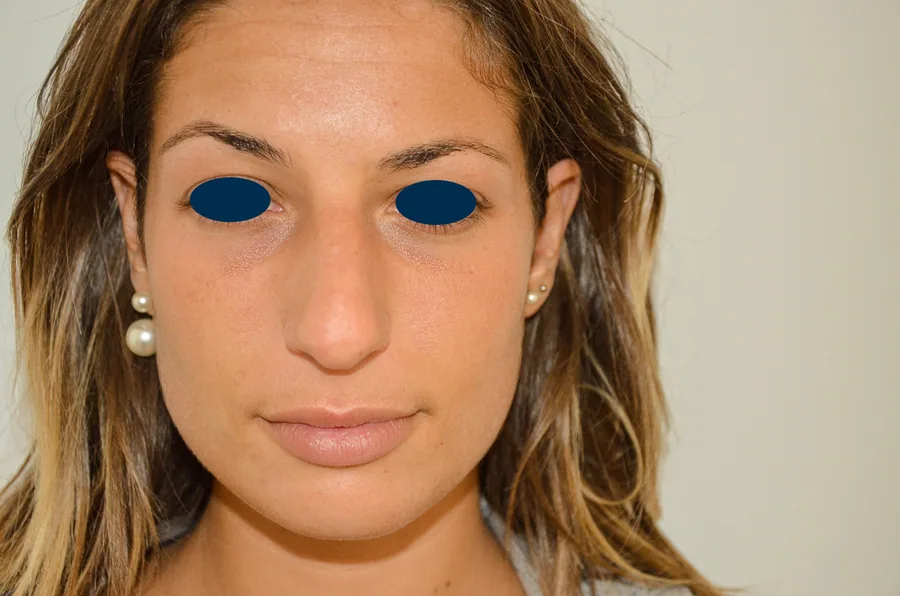
Patient after rhinoplasty — Dr Pulvermacker, Paris

Open or closed rhinoplasty: which approach?

In the great majority of cases I make the incision inside the nostrils, in the mucosa: this is the closed approach, which leaves no visible scar.

The open approach involves a short transverse incision on the columella, between the two nostrils. It gives wider exposure of the structures, at the cost of an external scar, and is reserved for situations where that exposure is indispensable.

Neither approach is superior in itself. The choice follows from what has to be done, not from a preference of school, and it is explained to you before the operation.

Should the nasal dorsum be removed or preserved?

A hump can be reduced in two ways. The first removes the excess bone and cartilage, then closes the vault that this resection has just opened. The second keeps the dorsum and lowers it by removing height underneath: this is preservation rhinoplasty.

Neither is superior in itself. The shape of the hump, the state of the septum and the thickness of the skin decide. The detail of that approach, its indications and its limits are set out on the page devoted to preservation rhinoplasty.

Can a nose already operated on be revised?

Yes, subject to conditions. A revision is not a second rhinoplasty: the landmarks have been altered, the skin has healed over a new framework, and the available cartilage may be lacking. It is decided on what can genuinely be corrected, and a proportion of requests ends in advice to abstain.

No revision is considered before one year after the previous operation. The course of the operation, the documents to gather and the increased risks are detailed on the page devoted to secondary rhinoplasty.

What is an ethnic rhinoplasty?

The term refers to a rhinoplasty adapted to particular morphological characteristics, for example in patients of African or Asian origin. The logic of the procedure is reversed compared with a reduction rhinoplasty.

The tip is refined, the size of the nostril openings is reduced, and projection — that is, height — is added at the dorsum, using a firm silicone implant or a graft taken from the patient: cartilage or bone.

The aim remains the same: to preserve the identity of the face rather than to conform it to a single model. A nose that no longer resembles the family of the person operated on is not a technical success, it is a contradiction in terms.

What is a non-surgical medical rhinoplasty?

In certain particular cases, a so-called medical rhinoplasty may be carried out with hyaluronic acid injections, to fill a depression or increase the projection of the tip.

This technique reduces nothing: it adds volume. It therefore does not replace a surgical rhinoplasty where a hump has to be removed or a broad nose refined. The result is immediate and the injections must be repeated roughly every eighteen months.

One point deserves stating: the region of the nose is supplied by small-calibre arteries, and accidental injection into one of them is the serious complication of this procedure. It calls for emergency management. That is why this act is the province of a doctor trained in the vascular anatomy of the face, with the enzyme that dissolves the product immediately to hand.

What is ultrasonic bone surgery?

The bony stage of a rhinoplasty — reducing a hump, narrowing the walls — was traditionally done with a rasp and an osteotome. For this I use an ultrasonic instrument, known as piezo surgery.

Its value rests on a simple property: ultrasonic vibration cuts bone and spares the soft tissues around it — lining, vessels, cartilage. A cutting instrument makes no such distinction.

In practice this allows finer work on the bone, and patients often report less marked bruising. It changes nothing about the timetable of the result: swelling at the tip follows the same course, and the final nose is still judged at one year.

How is the operation carried out?

Rhinoplasty is performed under general anaesthetic and most often requires one night in hospital. Where only the tip has to be treated, discharge on the same day is possible.

In every case the operation ends with a custom-made splint and with greased packing placed in the nasal passages.

Stopping smoking is required before and after the operation: nicotine reduces the blood supply to the skin and the mucosa, which delays healing and increases the risk of a healing problem.

What is the recovery like, day by day?

Rhinoseptoplasty is not a painful operation, even if the surgical procedure can sound impressive. It is a frequent source of apprehension, and the gap between what people imagine and what they actually experience is wide. The dominant discomfort is not pain but a blocked nose.

Day 1. The nasal packing is removed. Breathing remains congested for a few days because of swelling of the mucosa.

Days 2 to 7. Swelling and bruising of the eyelids, of very variable intensity from one person to another. Sleeping with the head raised reduces them. Blowing the nose is not allowed.

Days 8 to 10. The splint is removed. At that point the nose is usually very swollen: this is expected, and it is not the result. Many patients are unsettled at that precise moment; it is normal and it foretells nothing.

From day 10. The bruising has gone in most people. Returning to social and professional life is usually feasible.

Sport and glasses. Contact sports are not allowed for several weeks. Wearing glasses that press on the bridge is likewise deferred: the precise interval is given to you on discharge, and depends on the bone work carried out.

What follow-up is there after a rhinoplasty?

The splint comes off between the fifth and the seventh day, at the first review consultation. A second follows between day ten and day fourteen. In between, nurses handle local care and the anaesthetist checks that the prescribed pain relief is sufficient. Swelling of the nose settles more slowly than elsewhere on the face: the first weeks clear most of it, the tip takes longer. Manual lymphatic drainage and hyperbaric oxygen therapy may be offered where the surgeon judges them indicated. See post-operative care.

When can you fly again?

Here the limiting factor is neither thrombosis nor swelling alone: it is the nasal lining, still fragile, which tolerates two constraints specific to flying poorly.

The cabin is pressurised to the equivalent of 1,800 to 2,400 metres of altitude. That drop in pressure acts on tissues that are still healing. And the air is very dry, which dries out an already congested lining and weakens the vessels. The risk is bleeding.

The first week is incompatible with flying. The splint is still in place, swelling and bruising are at their peak, and this is the period when the risk of bleeding is highest of the whole recovery.

Short flight: seven to fourteen days, once the splint has been removed and in the absence of any bleeding.

Long-haul flight: the length of the journey itself becomes a factor. Beyond four hours it is prudent to wait two to three weeks. For a very long journey, and where a septal procedure or a cartilage graft has been combined with the operation, that interval may extend to four to six weeks: the lining stays fragile for longer.

During the flight: saline spray regularly, hydration, and no blowing of the nose.

If you are coming from far away, this is settled before booking, not after.

When is the result final?

The result appears gradually over the first few weeks and may be considered final at one year.

This long interval is due to the gradual resolution of swelling at the tip, the last area to settle. No revision should be undertaken before that point.

It should be taken in when deciding, not when growing impatient: rhinoplasty is surgery for the patient in both senses. The first three months give a direction, not a result.

What are the risks of a rhinoplasty?

Besides the risks associated with general anaesthesia, the main risk lies in imperfections of the result. A revision is sometimes needed; it should not be undertaken before one year.

The other risks, rarer, include bleeding in the first few hours, infection, transient disturbance of the sense of smell, a new or persistent breathing problem, and visible or palpable irregularities of the nasal dorsum.

Exceptional complications are set out in the information sheet of the French Society of Plastic, Reconstructive and Aesthetic Surgery, which is given and talked through at the consultation.

When should you contact the surgeon promptly?

In the event of heavy bleeding that does not stop, fever, sudden and intense pain, spreading redness, or disturbance of vision. The surgeon's professional number is given to you after the operation.

Is rhinoplasty reimbursed?

A purely aesthetic rhinoplasty is not reimbursed by French health insurance.

Where a deviated septum causes a documented breathing problem, the septal component may be eligible for partial reimbursement. The functional character is established on examination, not on assertion: the conditions are examined at the consultation.

Frequently asked questions

Does rhinoplasty leave a visible scar?

In the great majority of cases the incision is made by the closed approach, inside the nostrils: there is no visible scar. With the open approach, a short scar on the columella usually becomes very discreet once it has matured.

Does a rhinoplasty improve breathing?

Where a breathing problem is linked to a deviated septum, the procedure can correct it in the same operation. A purely aesthetic rhinoplasty does not set out to alter breathing, and the prior examination serves precisely to avoid impairing it.

From what age can a rhinoplasty be carried out?

The operation is considered once growth of the nasal structures is complete, generally around 16 to 17, with parental consent for a minor.

Can the result be seen in advance on a simulation?

A simulation helps mutual understanding: it puts images to words such as « refine » or « soften », which do not mean the same thing to everyone. It in no way constitutes a commitment as to the result, and I say so before showing it.

Is rhinoplasty painful?

Little. The dominant discomfort of the first few days is nasal obstruction, not pain, which responds to ordinary painkillers.

How much time off is needed?

Allow around ten days, the time for the splint to be removed and the bruising to fade. Some people return to non-public-facing work earlier.

Last updated: August 2026 · Medical content reviewed by Dr Benjamin Pulvermacker, qualified plastic surgeon in Paris 16.

Who this operation suits — and who it does not

It suits a precise, long-standing request — a hump, a drooping tip, a deviated nose — in someone whose facial growth is complete and who wants a nose in harmony with their face rather than a nose off the shelf. It does not suit expectations that are unrealistic or shaped by filtered images, a request that changes at every consultation, or certain situations of body dysmorphia where surgery deepens the distress instead of easing it: there, directing the patient towards appropriate support is part of the care.

Limits and specific risks

Skin thickness governs how refined the result can be: thick skin hides detail, very thin skin reveals all of it. Specific risks: residual imperfections, visible or palpable, asymmetry, new or persistent breathing difficulty, and the possibility of a revision (around one case in ten to fifteen in the literature, across all teams), at the earliest a year later. Swelling of the tip takes twelve to eighteen months to settle completely: rhinoplasty is surgery that requires patience.

A question about this procedure ?

Call 01 47 20 48 70

You are still hesitating

A consultation commits you to nothing.

A proportion of consultations end with no indication, or with a decision to wait. These are normal outcomes, and they are said to your face.

What happens at a first consultation →

Consultation

Let us talk about your plan

The secretariat answers from Monday to Friday, 9 a.m. to 6 p.m.

You have decided

Request an appointment

Give your availability, the practice offers you a slot.

My availability

You would rather speak

Be called back

Leave a number and a time. The secretariat calls you within 48 working hours.

Be called back

You are gathering information

Write to the practice

A question, without an appointment. The secretariat passes it on, answer within 48 working hours.

Ask a question

Or by telephone : 01 47 20 48 70Exchanges are covered by medical confidentiality.

A detailed quotation is compulsorily given at the consultation. A statutory reflection period of fifteen days runs from the moment it is handed over.

What results can be expected ?

Every situation is particular: these photographs illustrate results obtained, they do not predict yours.

Before photo: rhinoplasty — Dr Pulvermacker, Paris
Before
After photo: rhinoplasty — Dr Pulvermacker, Paris
After
Before photo: rhinoplasty — Dr Pulvermacker, Paris
Before
After photo: rhinoplasty — Dr Pulvermacker, Paris
After
Before photo: rhinoplasty — Dr Pulvermacker, Paris
Before
After photo: rhinoplasty — Dr Pulvermacker, Paris
After

See all the results

Contact the practice

The secretariat answers from Monday to Friday. You may also write : we call you back within 48 working hours.

Rhinoplasty in Paris 16 — a question about this procedure ?Be called backWrite01 47 20 48 70
Call Write